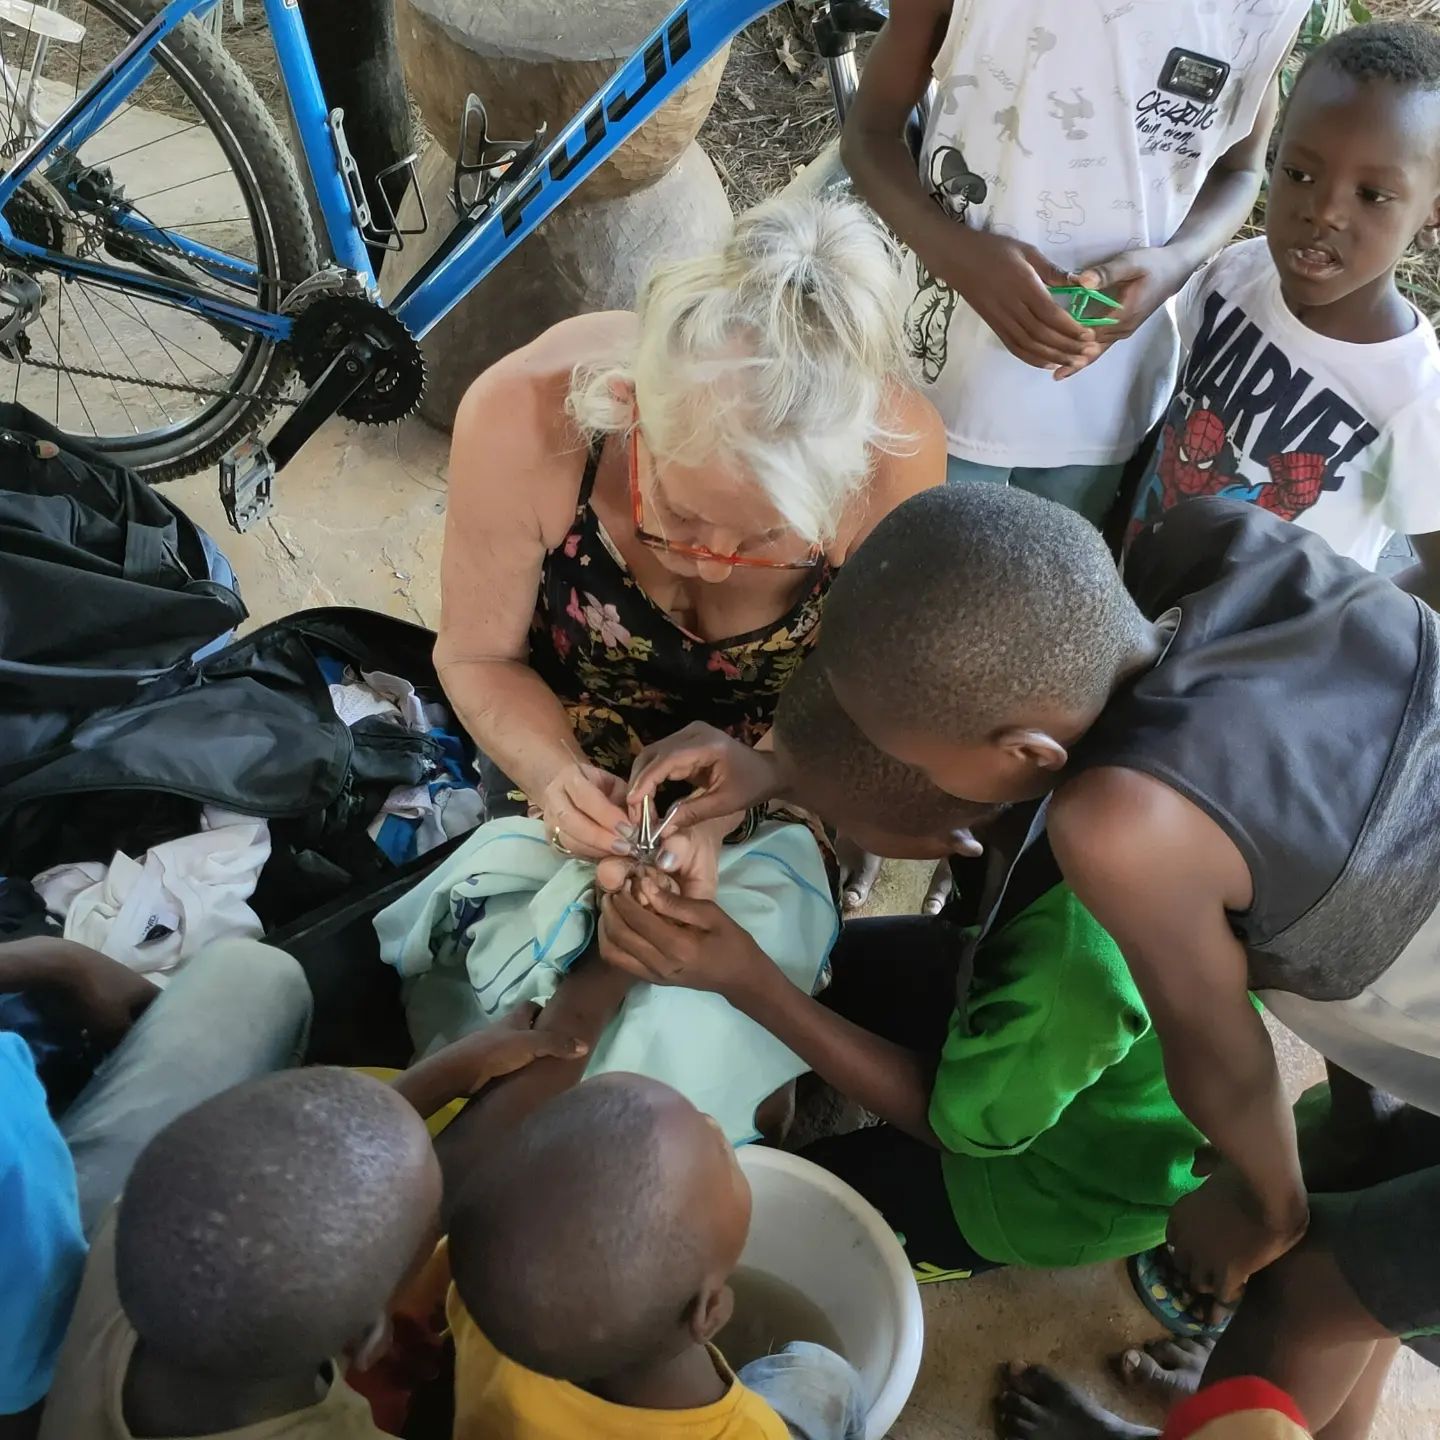Giant jiggers refer to heavily engorged female Tunga penetrans fleas, commonly known as chigoe fleas or sand fleas, which burrow into the skin of warm-blooded hosts and swell dramatically as they produce eggs. This parasitic infection, known as tungiasis, presents significant public health challenges in endemic tropical and subtropical regions, requiring prompt medical intervention, proper hygiene practices, and community-wide prevention strategies to avoid severe secondary complications.
Understanding the Parasite: What Are Giant Jiggers?
To understand what giant jiggers are, one must look at the life cycle and biological behavior of Tunga penetrans. Unlike typical fleas that jump onto a host, feed, and jump off, the female chigoe flea behaves as an ectoparasite that penetrates the epidermis of its host—most commonly humans, pigs, and dogs—to complete its reproductive cycle.
The term "giant jigger" typically describes a female chigoe flea that has successfully burrowed into the stratum corneum and undergone nesidioblastosis or extreme abdominal distension (neosomy). Once embedded, the flea's abdomen swells up to the size of a pea—often reaching dimensions of several millimeters—as it engorges on blood and develops hundreds of eggs.
The primary habitat of Tunga penetrans consists of sandy, dry soils found in impoverished rural communities, beaches, and areas with poor housing infrastructure. The fleas thrive in warm, dry climates and are particularly prevalent in parts of sub-Saharan Africa, Latin America, and the Caribbean. Understanding the ecological niche of the parasite is essential for implementing effective local control measures and personal protective habits.
The Life Cycle of Tunga penetrans
The life cycle of the chigoe flea consists of four distinct stages: egg, larva, pupa, and adult. Each stage presents unique vulnerabilities and environmental interactions that influence the spread of tungiasis.
- Egg Stage: After mating on or within the host, the female flea expels 100 to 200 eggs over a period of one to three weeks. Because the flea is embedded in the skin, these eggs typically fall out onto the ground or are expelled when the lesion ruptures.
- Larval Stage: Within three to four days, eggs hatch into larvae in sandy soil, feeding on organic debris and detritus.
- Pupal Stage: The larvae spin cocoons, transforming into pupae within approximately one to two weeks, depending on ambient temperature and humidity.
- Adult Stage: Emerging adult fleas seek out a host by jumping short distances from the ground. Both males and unfertilized females feed intermittently on blood, but only the fertilized female penetrates the host's skin.
| Life Cycle Stage | Duration | Primary Activity | Environment |
|---|---|---|---|
| Egg | 3–4 days to hatch | Expelled from embedded female | Sandy soil / floor |
| Larva | 7–10 days | Feeding on organic debris | Dry soil, dust |
| Pupa | 7–14 days | Metamorphosis inside cocoon | Soil / sub-floor layers |
| Adult | Weeks to months | Seeking hosts, mating, embedding | Ground surface / Host skin |
Clinical Manifestations and Symptoms of Tungiasis
When a female Tunga penetrans penetrates the skin, it usually targets areas of the foot, such as the periungual region (around the toenails), the soles, and the interdigital spaces, though hands and other body parts can also be affected if they come into contact with contaminated soil.
The progression of symptoms follows a well-documented timeline, often classified using the Fortaleza classification system to grade the severity of the lesion:
- Stage I & II: Penetration occurs, causing a localized itching sensation, slight pain, and a tiny black dot visible in the center of a small erythematous (red) papule. As the flea feeds and grows over the first few days, the lesion enlarges.
- Stage III: The flea reaches its maximum size ("giant jigger" phase). A prominent white circular patch with a central dark spot (the posterior abdominal segements of the flea through which it breathes, defecates, and releases eggs) becomes clearly visible. Intense inflammation, pain, and throbbing occur.
- Stage IV: The parasite dies in situ after releasing its eggs. The lesion undergoes involution, turning into a brown-black crust or a residual scar as the dead flea is naturally sloughed off or surgically removed.
Secondary Complications
While an isolated tungiasis lesion can be painful, chronic and heavy infestations (hyperinfestation) lead to severe pathological consequences. Because the skin barrier is breached, patients are highly susceptible to secondary bacterial infections, including:
- Tetanus: A major risk in areas with low vaccination coverage, often fatal without prophylaxis.
- Cellulitis and Abscess Formation: Bacterial invasion leading to severe swelling, pus accumulation, and deep tissue damage.
- Gangrene and Auto-Amputation: In extreme cases, vascular compromise and necrosis can lead to the loss of toes or digits.
- Walking Impairment: Severe pain in the feet alters gait, leading to secondary musculoskeletal issues and chronic disability.
Medical Management and Treatment Protocols
Standard medical protocols for treating tungiasis focus on safely removing the parasite, managing inflammation, and preventing secondary infections.
Professional Extraction
The definitive treatment for an embedded chigoe flea is surgical extraction under sterile conditions. Trained healthcare professionals use sterile instruments, such as a blunt needle or forceps, to carefully widen the entry hole in the skin and extract the intact flea without rupturing it. Rupturing the flea inside the tissue can trigger severe inflammatory reactions due to the release of parasite antigens and remaining eggs.
Topical and Systemic Treatments
- Antiseptics and Antibiotics: Topical antibiotic ointments or systemic antibiotics are prescribed if secondary bacterial infections are present.
- Tetanus Prophylaxis: Given the high risk of Clostridium tetani infection through open skin lesions, patients must receive a tetanus toxoid booster or immunoglobulin according to their vaccination history.
- Repellents and Botanical Oils: Research has investigated the efficacy of topical treatments containing natural oils (such as coconut oil combined with jojoba, aloe vera, and neem) that suffocate the embedded flea by blocking its respiratory spiracles, causing the parasite to die and be expelled naturally.
| Treatment Method | Mechanism | Advantages | Risks / Limitations |
|---|---|---|---|
| Surgical Extraction | Manual removal via sterile needle/forceps | Immediate parasite elimination | Risk of rupture and infection if unsterile |
| Topical Suffocation (Oils) | Blocks respiratory spiracles | Non-invasive, easy to apply in community settings | Slower resolution time; requires repeated application |
| Antibiotic Therapy | Combats secondary bacterial pathogens | Prevents cellulitis, sepsis, and severe morbidity | Does not remove the parasite itself |
Prevention and Public Health Strategies
Preventing giant jigger infestations requires a combination of personal protective behaviors, environmental modifications, and socioeconomic improvements within endemic regions.
Personal Protection
- Footwear: Consistently wearing closed-toe shoes, boots, or sandals significantly reduces the direct contact of bare skin with contaminated soil.
- Topical Repellents: Applying natural or chemical insect repellents to the feet and ankles can deter host-seeking fleas.
- Avoiding High-Risk Areas: Minimizing direct sitting or walking on dry, sandy floors in endemic households without concrete or sealed flooring.
Environmental Control and Community Interventions
- Flooring Improvements: Upgrading traditional dirt floors to concrete or tiled surfaces prevents the life cycle of the flea from completing, as larvae cannot easily develop in hard, sealed surfaces.
- Animal Husbandry: Keeping domestic animals—such as dogs and pigs, which act as important animal reservoirs for Tunga penetrans—away from human living quarters and treating them with appropriate antiparasitic agents.
- Community Education: Informing local populations about early signs of infection, discouraging the dangerous practice of sharing non-sterile needles for extraction, and promoting prompt treatment.
Frequently Asked Questions About Giant Jiggers
What causes a jigger to become giant?
A jigger becomes "giant" when a fertilized female Tunga penetrans flea burrows into the skin and undergoes neosomy. Over one to two weeks, its abdomen swells drastically as it engorges on blood and matures hundreds of eggs, expanding to the size of a small pea.
Can giant jiggers jump onto people?
Adult chigoe fleas in the soil can jump short vertical distances—typically up to 20 centimeters—to reach a host's feet or ankles. Once they land on a host, they crawl upward to find a suitable feeding and penetration site.
Is it safe to dig out a jigger with a needle at home?
Removing a jigger at home using non-sterile needles or pins is strongly discouraged. This practice frequently leads to the accidental rupture of the flea, severe secondary bacterial infections, and transmission of bloodborne pathogens. Professional or sterile extraction is always recommended.
Are animals affected by giant jiggers?
Yes, domestic animals such as dogs, cats, pigs, and rats serve as important animal reservoirs for Tunga penetrans. Treating infected animals is vital for breaking the transmission cycle in endemic communities.
How can I prevent tungiasis when traveling to endemic areas?
The most effective prevention method is wearing closed shoes at all times when walking on sandy or dusty soil, maintaining good personal hygiene, inspecting feet daily after outdoor exposure, and avoiding walking barefoot indoors in unpaved buildings.
Conclusion and Next Actions
Giant jiggers present a serious medical and social challenge in endemic regions, causing significant pain, disability, and secondary infections if left untreated. Understanding the life cycle, recognizing early clinical symptoms, and utilizing professional extraction methods are essential steps in managing the condition. For individuals living in or traveling to high-risk areas, prioritizing footwear, maintaining clean living environments, and seeking prompt medical care for skin lesions remain the most effective defenses against tungiasis.