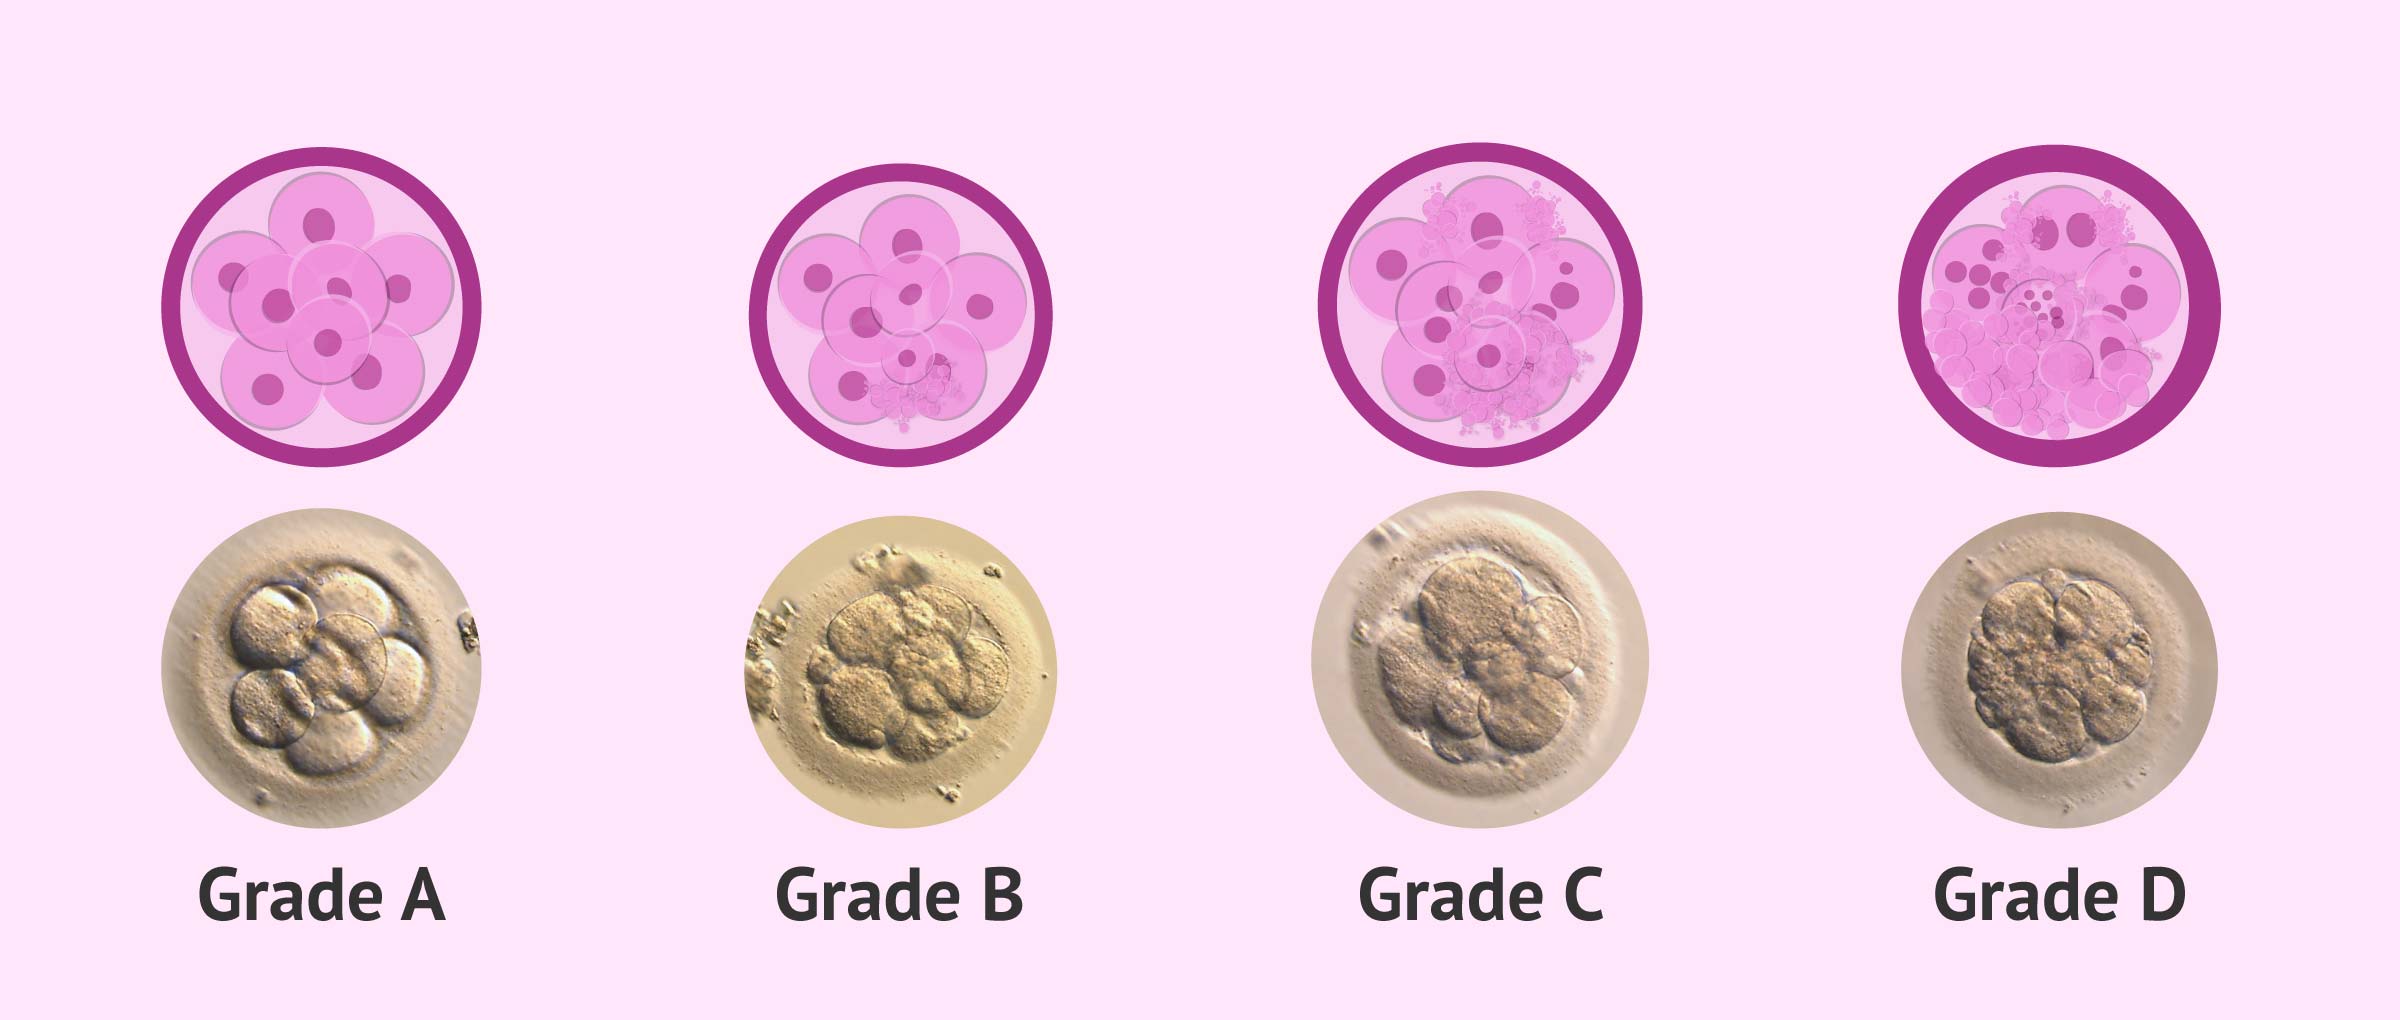
An embryo on day 4 of development, known as the morula stage, represents a critical transition point in assisted reproductive technology (ART). At this stage, the embryo consists of 8 to 16 cells that have undergone compaction, forming a dense ball of cells. While day 3 (cleavage stage) and day 5 (blastocyst stage) are more commonly discussed in clinical settings, understanding day 4 morphology provides essential insights into embryo viability and the potential for successful implantation.
The Biological Progression: From Cleavage to Compaction
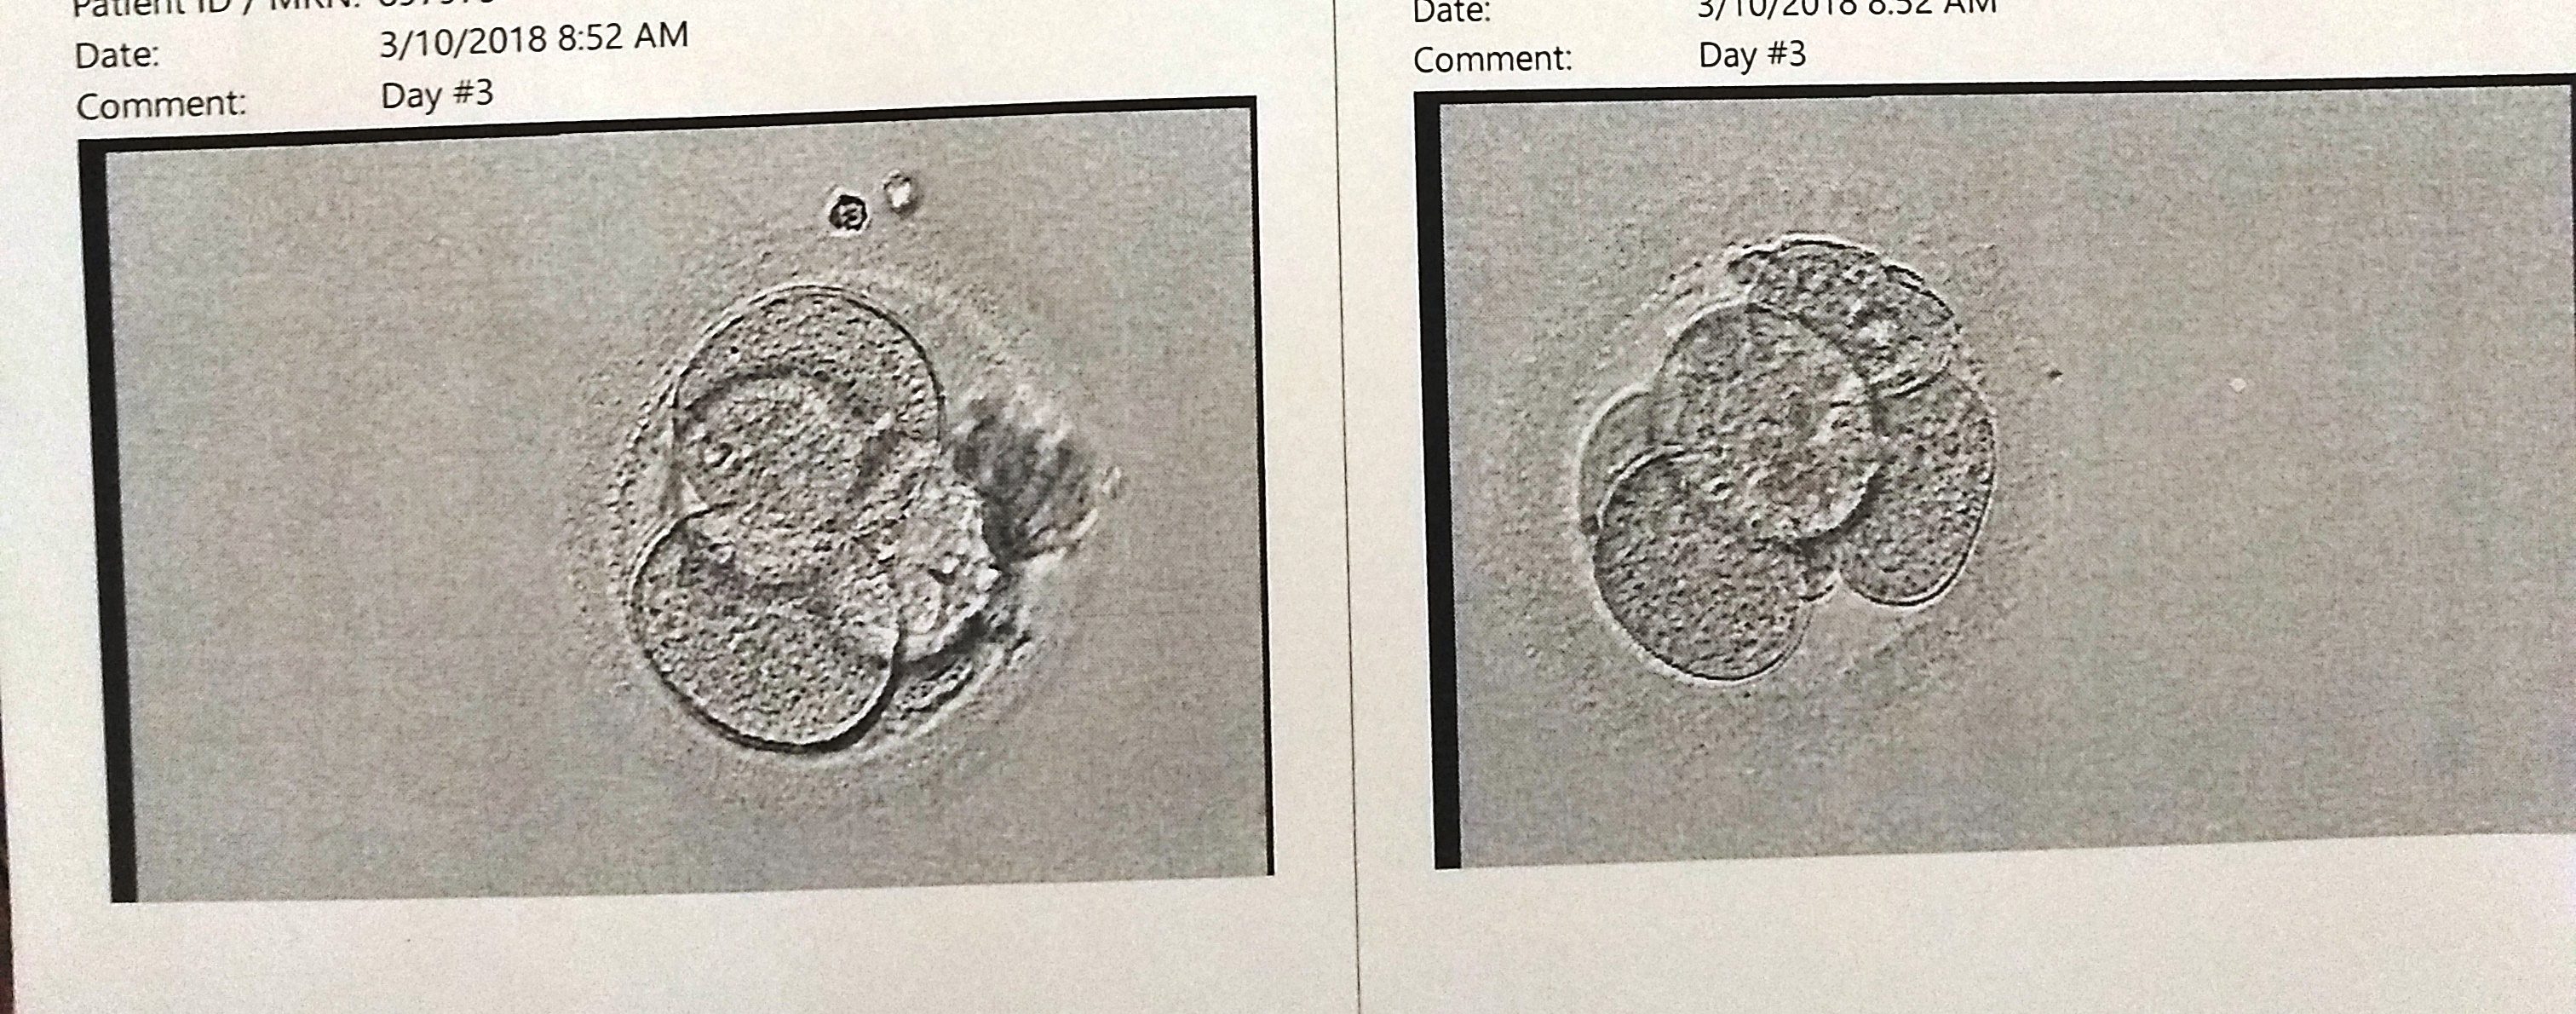
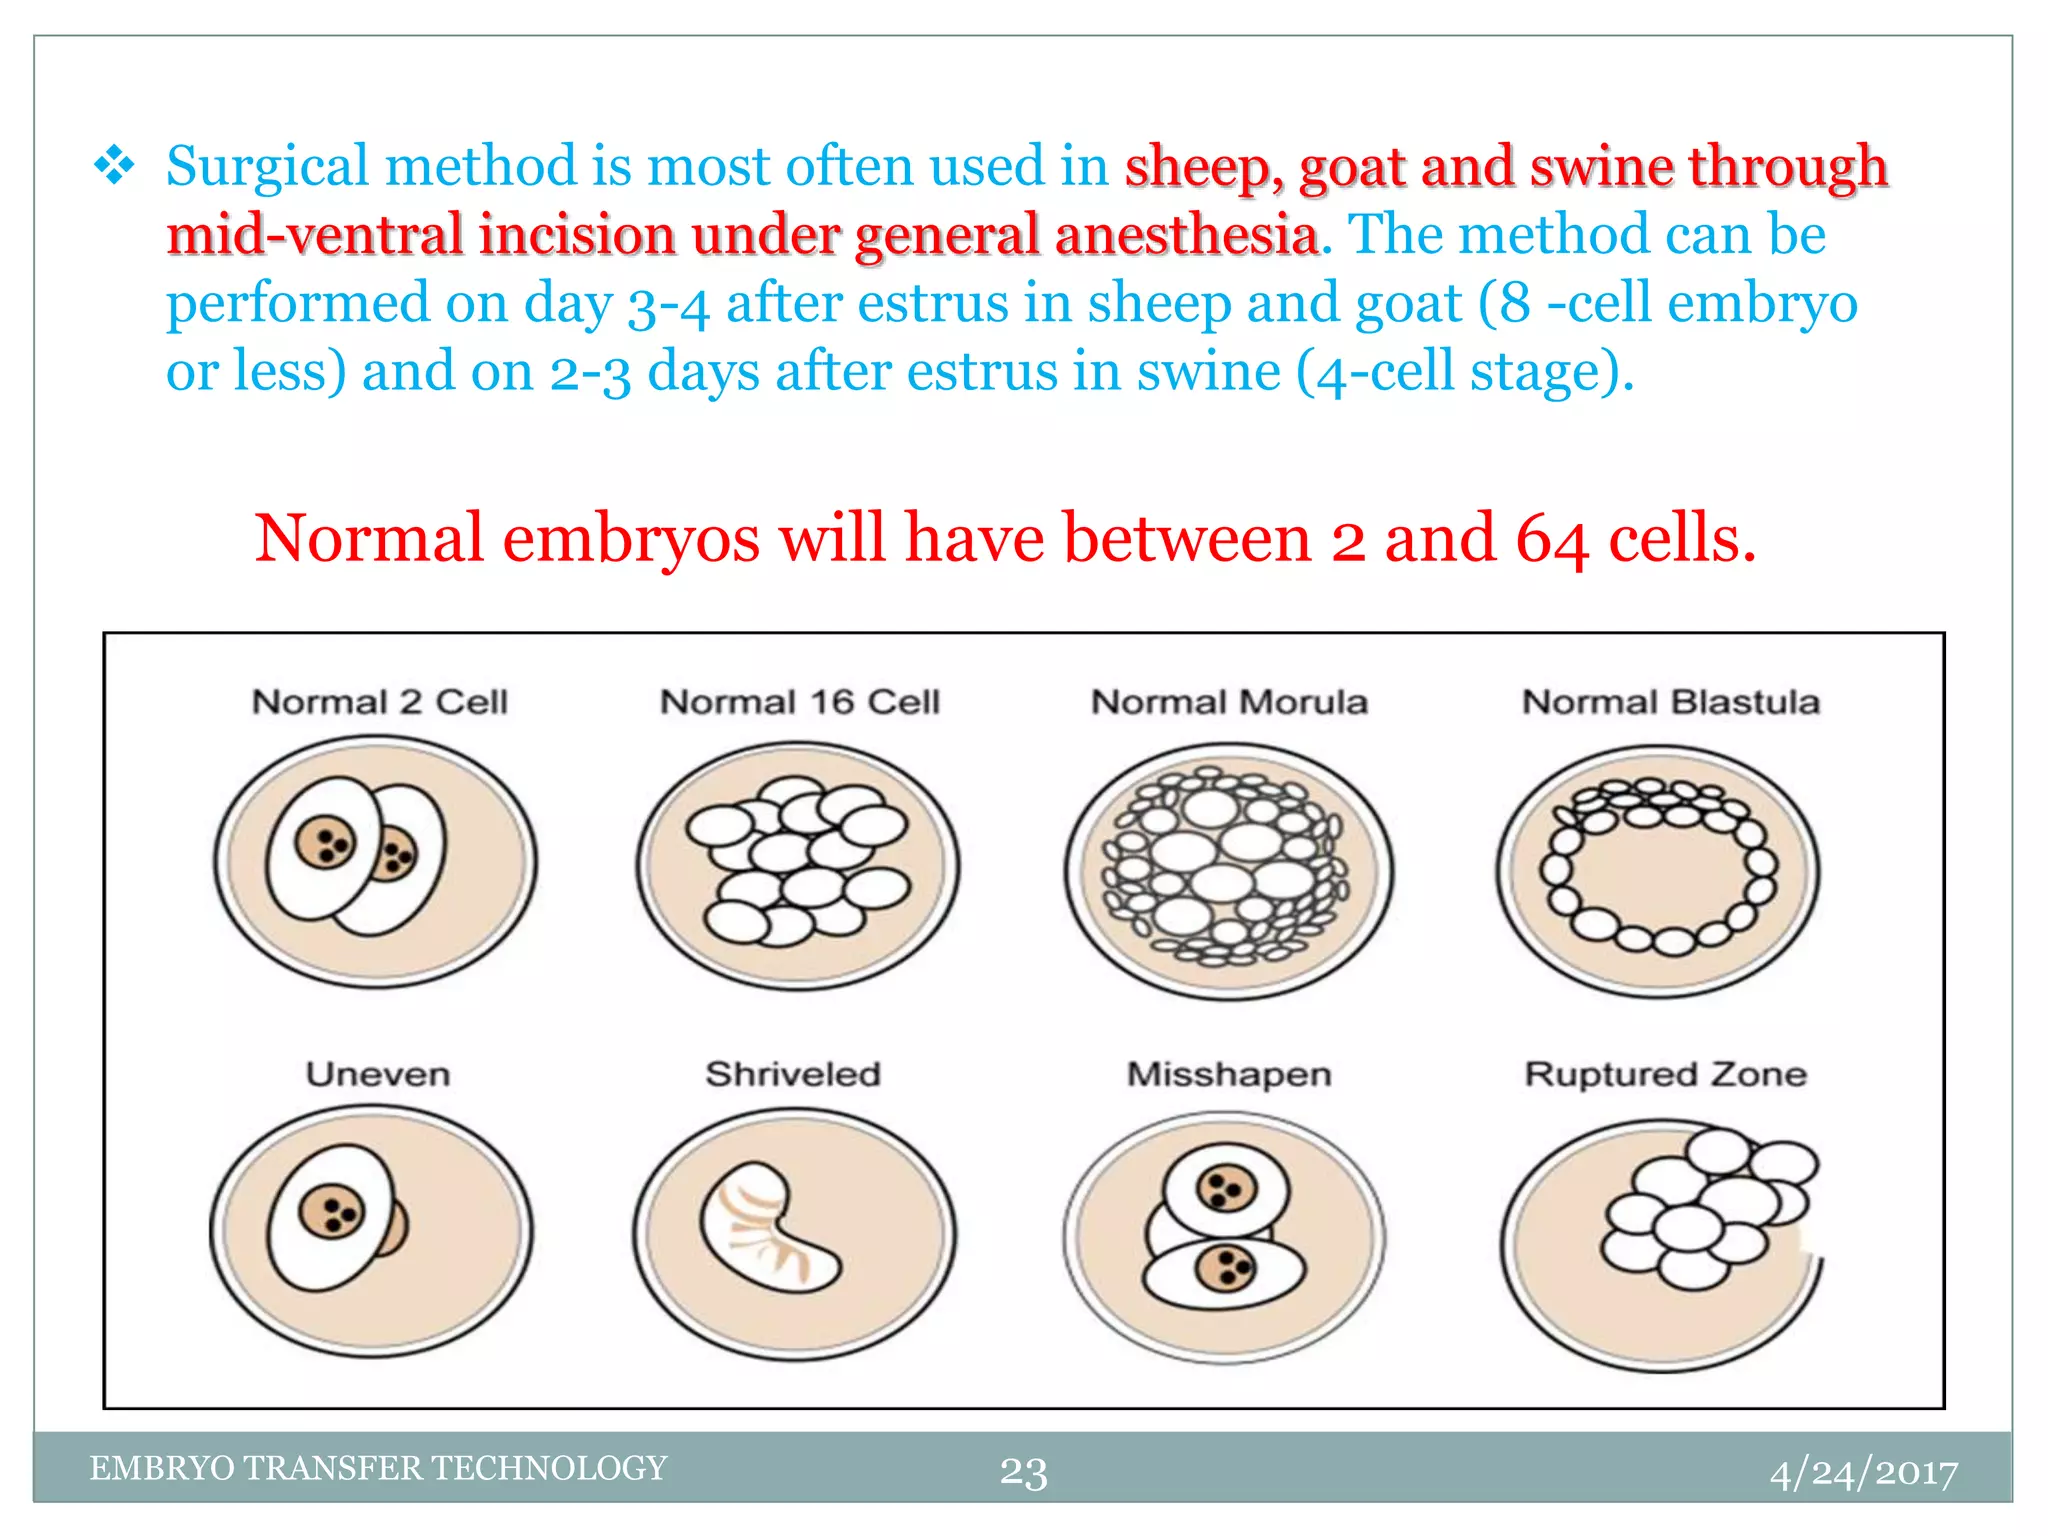
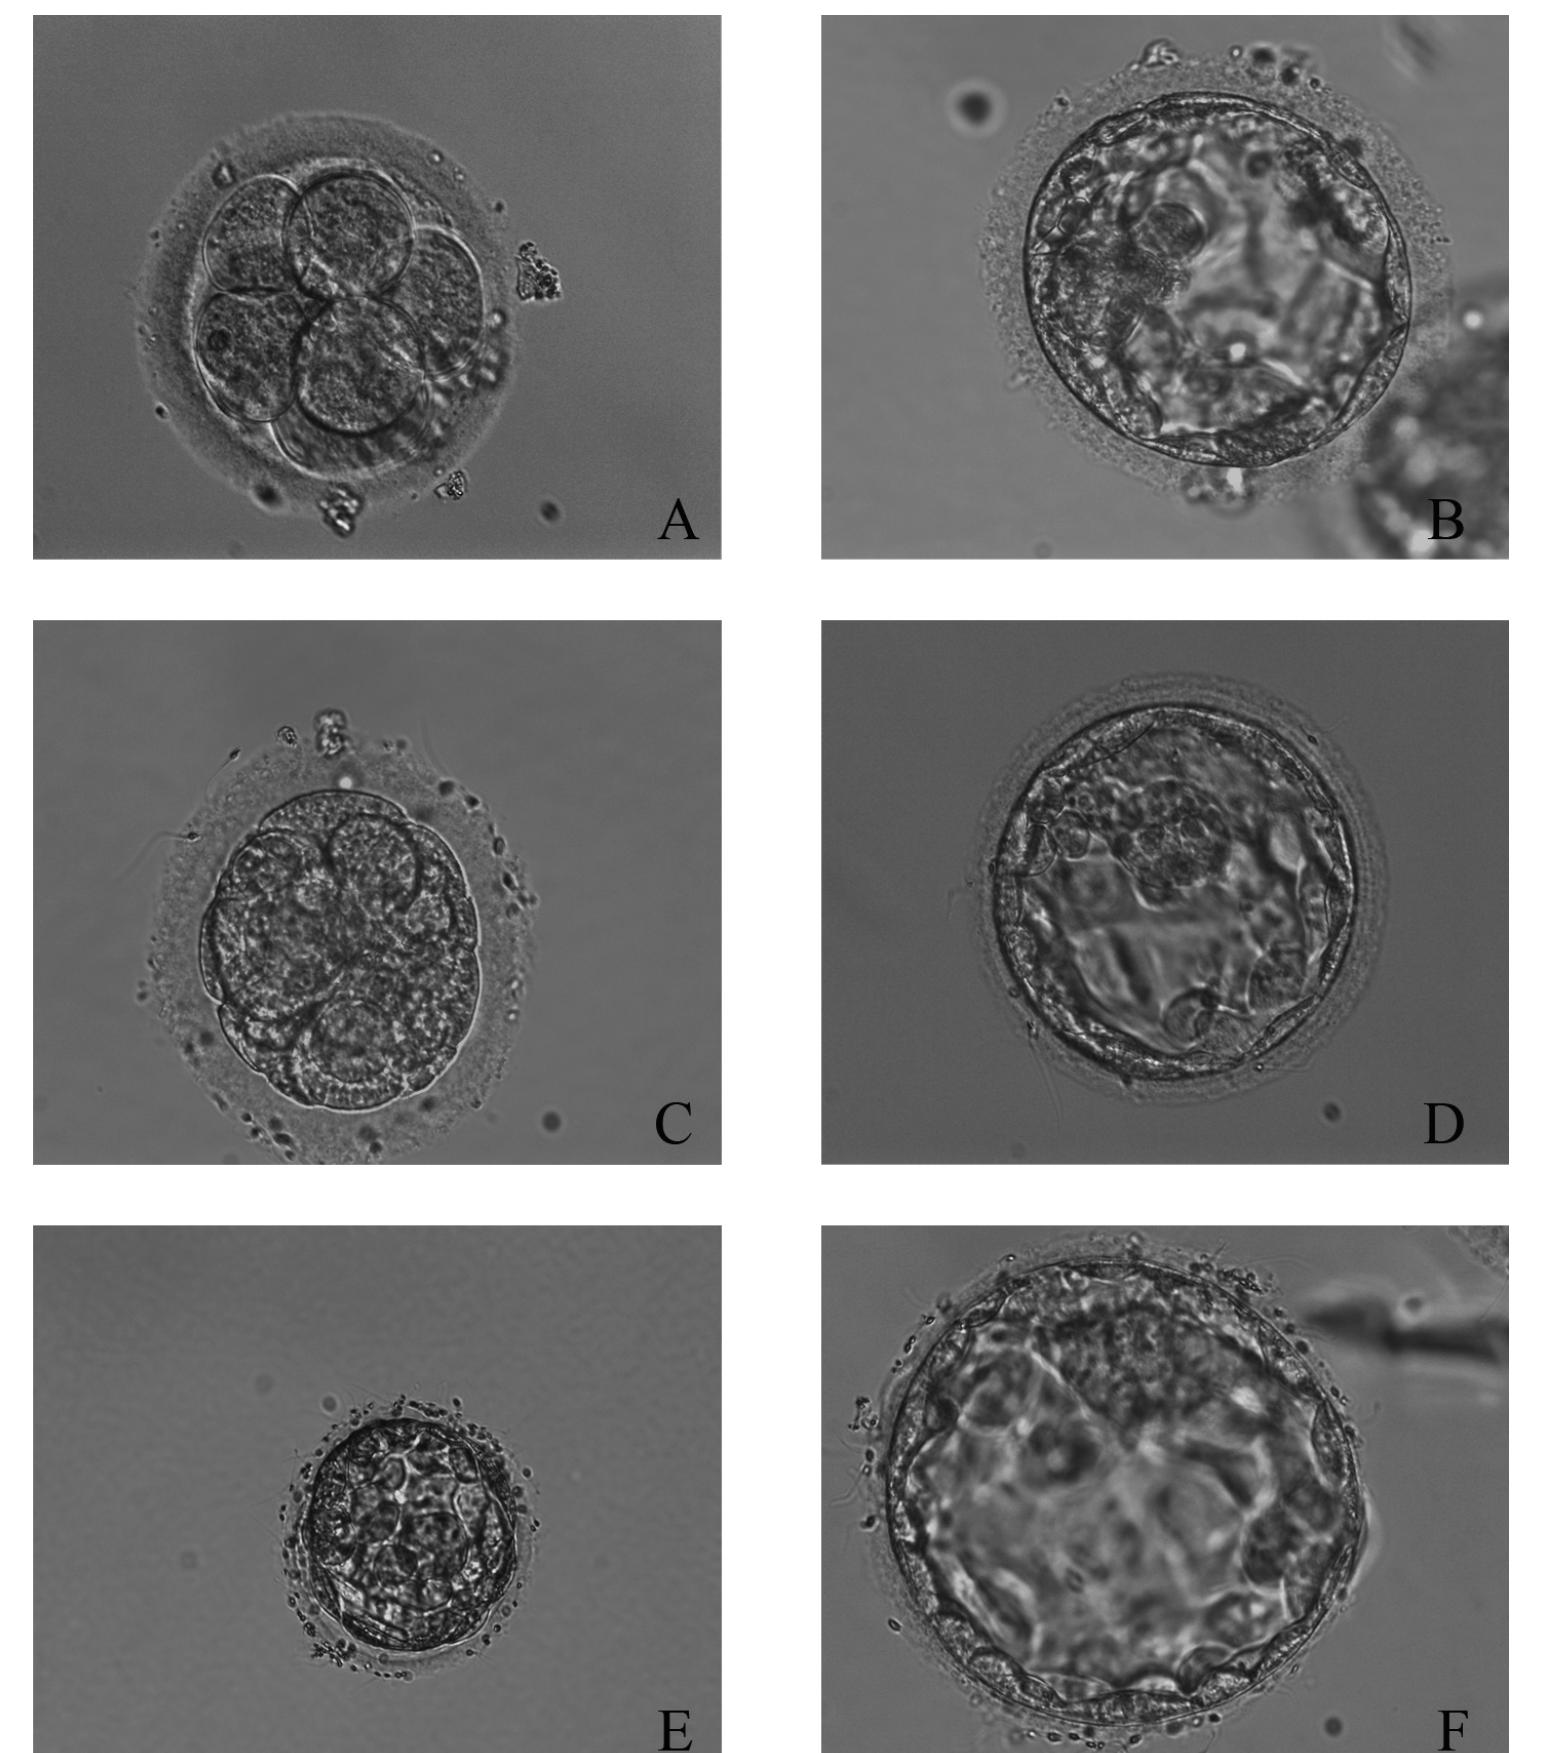
To understand why day 4 is a pivotal time, one must examine the progression of the human embryo following fertilization. On day 1, the zygote is a single cell. By day 2, it typically reaches the 2- to 4-cell stage, and by day 3, it progresses to 6 to 8 cells. These early divisions are primarily driven by maternal RNA stored within the oocyte.
As the embryo approaches day 4, a transformative process called compaction occurs. During this phase, the individual blastomeres (cells) maximize their surface area contact with one another. They adhere tightly via tight junctions and gap junctions. This creates an internal environment distinct from the external surroundings, a necessary precursor to the formation of the blastocoel cavity that will define the day 5 blastocyst. The transition from a loose collection of cells to a tightly knit morula is a vital indicator that the embryo’s genome has successfully activated and is taking control of development.
Assessing Embryo Quality on Day 4
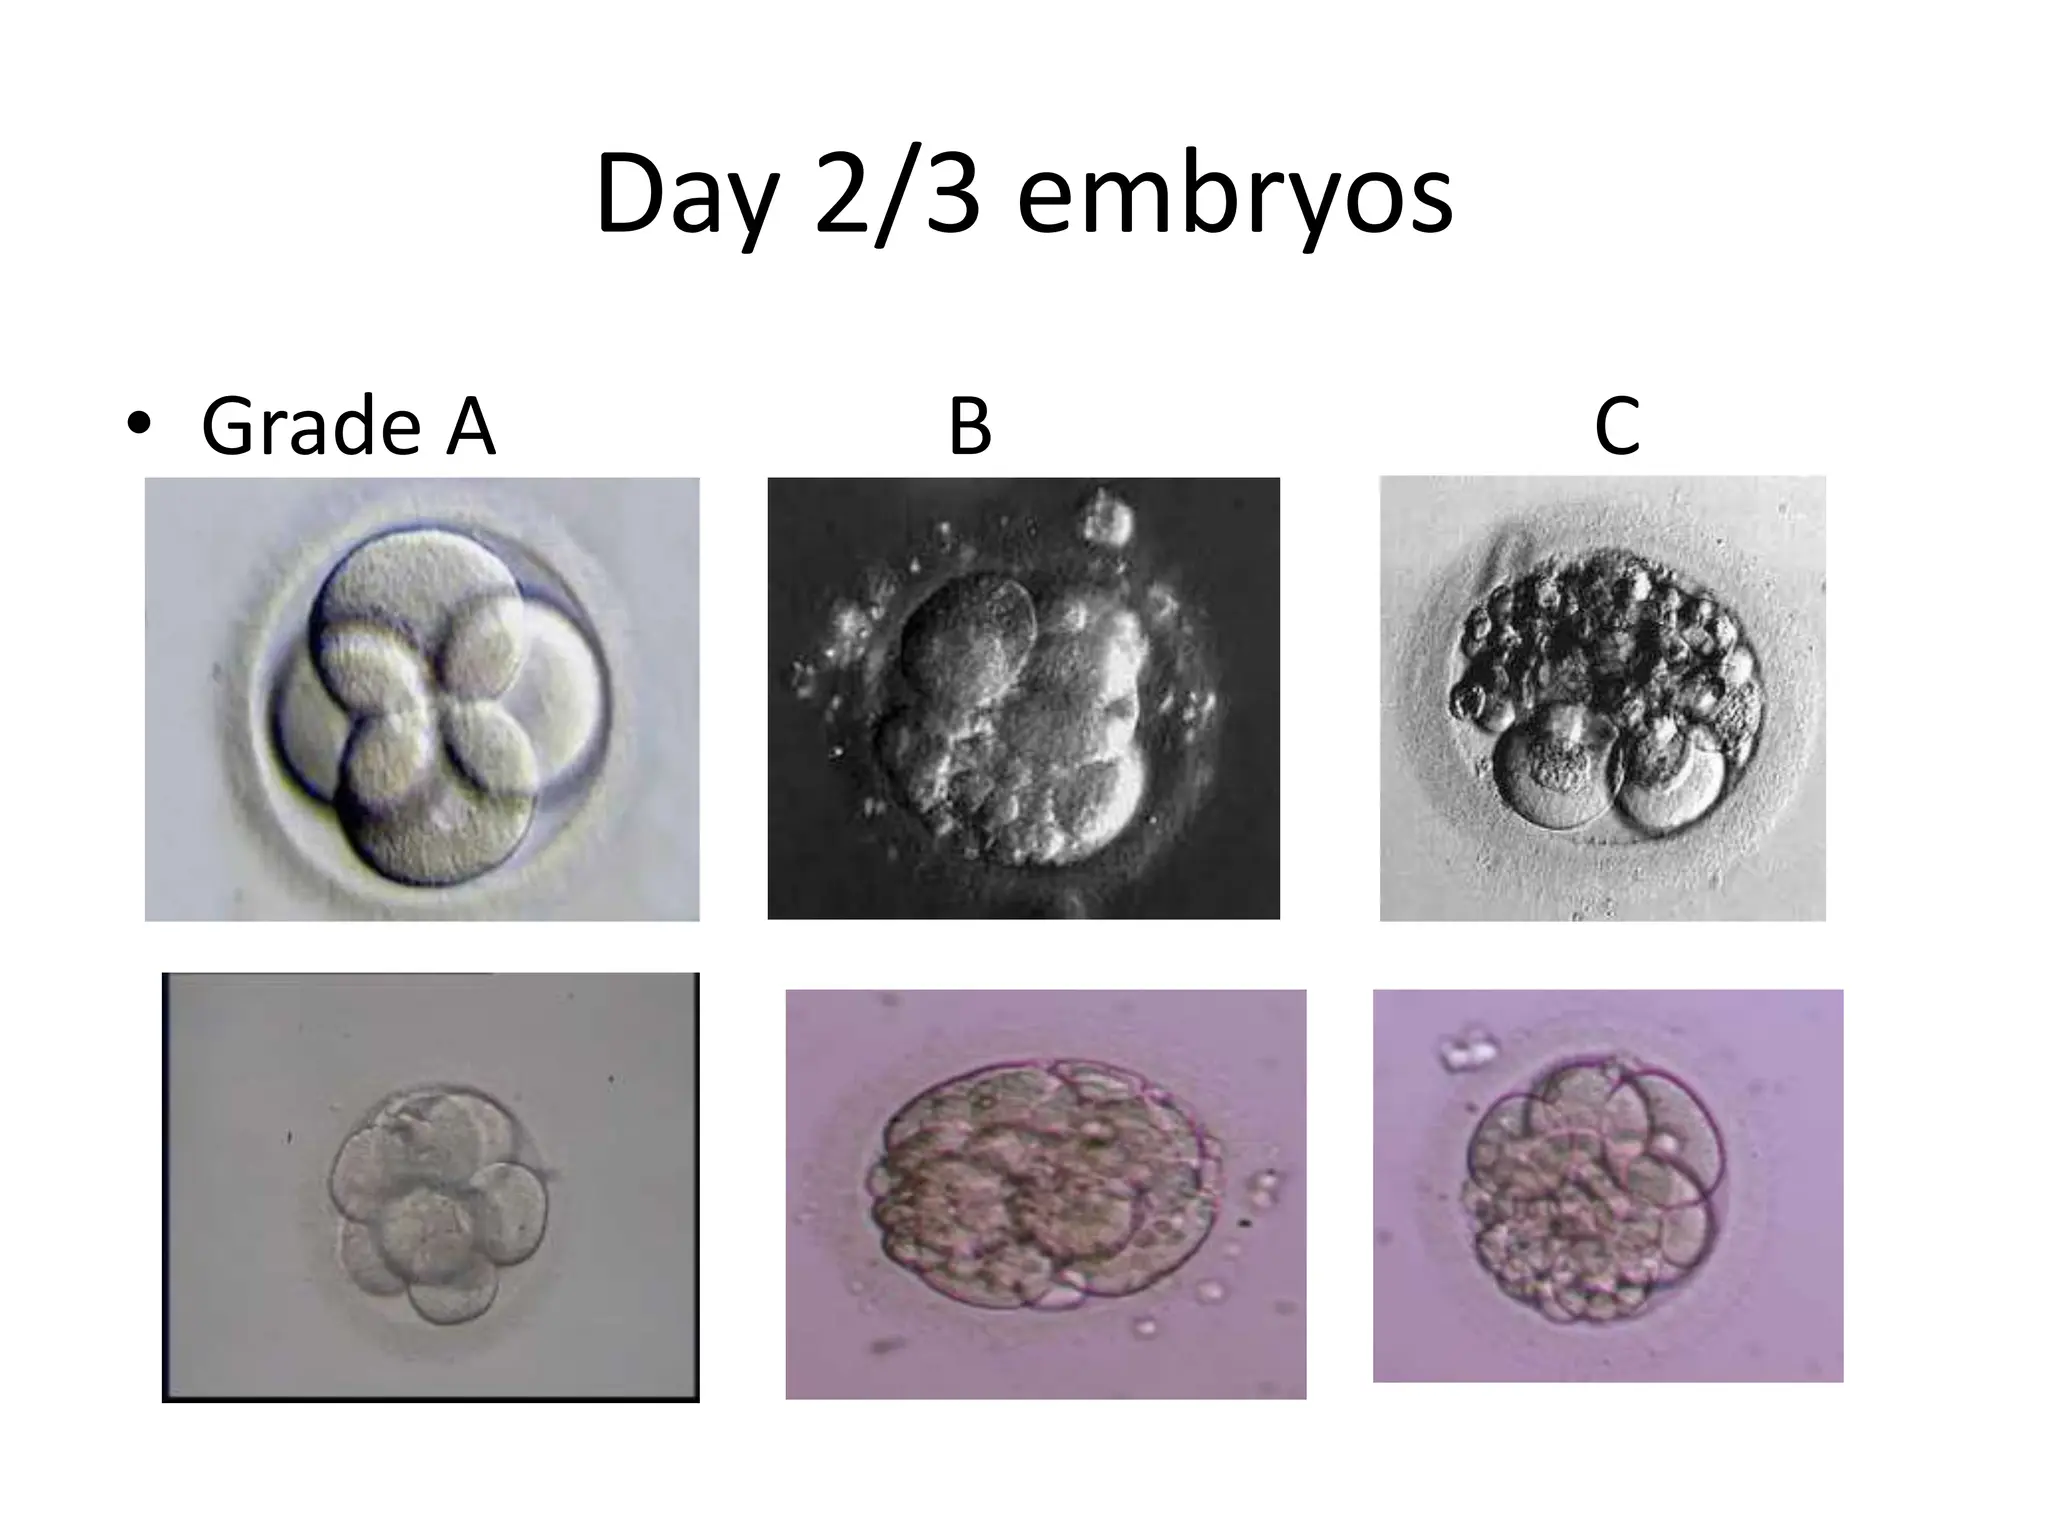
Clinical embryologists evaluate day 4 embryos by observing the degree of compaction and the presence of cellular fragmentation. Because the cells are so tightly packed, assessing individual cell symmetry—a primary metric for day 2 and day 3 embryos—becomes impossible. Instead, the focus shifts to the overall integrity of the morula.
A high-quality day 4 embryo should exhibit:
- Advanced Compaction: Most, if not all, cells should be indistinguishable, appearing as a solid, unified structure.
- Minimal Fragmentation: While some small amount of cytoplasmic debris is common, large areas of fragmentation can signal suboptimal developmental potential.
- Appropriate Size: The overall size of the morula should remain consistent with the zona pellucida, the outer protective shell of the embryo.
If an embryo fails to compact by day 4, it is often categorized as "arrested" or "slow-developing." Such embryos have a significantly lower statistical probability of reaching the blastocyst stage or resulting in a clinical pregnancy.
Clinical Practice: Why Day 4 Transfers Are Rare
In contemporary IVF practice, the vast majority of embryo transfers are performed either on day 3 (cleavage stage) or day 5/6 (blastocyst stage). Day 4 transfers are exceptionally rare for several scientific and logistical reasons.
- The "In-Between" Nature: Day 4 is a phase of rapid internal reorganization. Because the embryo is undergoing compaction, it is difficult to grade its developmental potential accurately compared to the distinct morphological markers available at the blastocyst stage.
- Extended Culture Capabilities: With modern laboratory media and incubator technology, clinics can reliably grow embryos to the blastocyst stage (day 5 or 6). This allows for "natural selection" in vitro; only embryos capable of reaching the blastocyst stage are selected for transfer, which generally leads to higher implantation rates per embryo transferred.
- Synchrony with the Endometrium: Natural conception involves the embryo arriving in the uterus at the blastocyst stage. Transferring on day 5 aligns more closely with the body's natural cycle, where the uterine lining (endometrium) is primed for the arrival of a blastocyst.
Comparative Development Stages in IVF
The following table summarizes the typical progression and clinical focus of early-stage embryos within an IVF cycle.
| Stage | Timing | Cellular Status | Clinical Focus |
|---|---|---|---|
| Day 2 | 48 hours post-fertilization | 2–4 cells | Initial cleavage and symmetry |
| Day 3 | 72 hours post-fertilization | 6–8 cells | Cell count, fragmentation, symmetry |
| Day 4 | 96 hours post-fertilization | Morula (Compacted) | Degree of compaction and integrity |
| Day 5 | 120 hours post-fertilization | Blastocyst | Trophoblast and Inner Cell Mass grading |
Challenges and Limitations of Day 4 Culture
While day 4 is a developmental checkpoint, it is also a period of high metabolic transition. The embryo is shifting its energy reliance from maternal reserves to its own mitochondrial activity. This metabolic shift is one reason why some embryos that look perfect on day 3 fail to compact on day 4.
Common issues observed during this window include:
- Developmental Arrest: The embryo stops dividing, often due to chromosomal abnormalities that prevent the transition from maternal to embryonic genetic control.
- Asynchronous Compaction: The embryo may appear "loose," where only some cells have compacted. This is often associated with lower viability.
- Degeneration: In some cases, the cells simply begin to lose integrity, signaling the end of that specific embryo's developmental timeline.
It is important to note that embryos that progress slowly to the morula stage on day 4 but successfully reach the blastocyst stage by day 5 or 6 can still result in healthy pregnancies. However, embryos that remain as loose, uncompacted cells by the end of day 4 are rarely chosen for transfer or biopsy.
The Role of Genetic Testing (PGT-A)
When clinics utilize Preimplantation Genetic Testing for Aneuploidy (PGT-A), the biopsy is almost exclusively performed on day 5 or 6 blastocysts. A day 4 morula is generally not considered suitable for biopsy because the cells are too tightly packed to allow for the safe removal of samples without damaging the cell mass. Furthermore, the molecular machinery of the morula is still transitioning, making the sample potentially less representative of the embryo's future chromosomal status.
Frequently Asked Questions
1. If my embryos are at the morula stage on day 4, does this mean they are healthy? Reaching the morula stage on day 4 is a positive sign that the embryo is proceeding through development. However, it does not guarantee chromosomal normality or successful implantation. It confirms that the embryo has reached a necessary developmental milestone in vitro.
2. Why don't doctors transfer embryos on day 4? Transferring on day 4 is generally avoided because it occurs during a period of transition where the embryo is difficult to grade. Waiting until day 5 (blastocyst stage) allows the embryologist to better identify the embryos with the highest implantation potential, thereby increasing the chance of success.
3. Is it common for all embryos to reach the morula stage by day 4? No. It is common for a cohort of embryos to exhibit "attrition," where only a subset of fertilized eggs will reach the morula or blastocyst stage. Factors such as maternal age, sperm quality, and lab conditions all influence these rates.
4. What should I ask my embryologist about my day 4 embryos? You should ask about the "compaction rate" of your cohort—specifically, what percentage of the embryos reached the morula stage. This provides a snapshot of how well the embryos are tolerating the laboratory environment.
5. Does a "slow" day 4 morula mean the embryo is abnormal? Not necessarily. While rapid progression is often correlated with higher success rates, some embryos are simply slower to undergo compaction. Provided they reach the blastocyst stage by day 5 or 6, they may still be viable.
Next Steps and Professional Guidance
If you are currently undergoing an IVF cycle and are concerned about your embryo development, the most constructive step is to request a detailed report from your embryology lab. Specifically, inquire about the proportion of embryos that successfully reached the compacted morula stage by day 4.
This information can help your fertility specialist determine the next course of action, whether that involves continuing the culture to day 5 for potential transfer or considering a different approach in a future cycle. Always consult with a reproductive endocrinologist regarding the specific outcomes of your cycle, as they can provide context based on your individual medical history and the results of your laboratory team. Medical decisions regarding fertility treatments should be individualized, and laboratory success metrics should always be interpreted in the context of a patient's broader clinical profile.