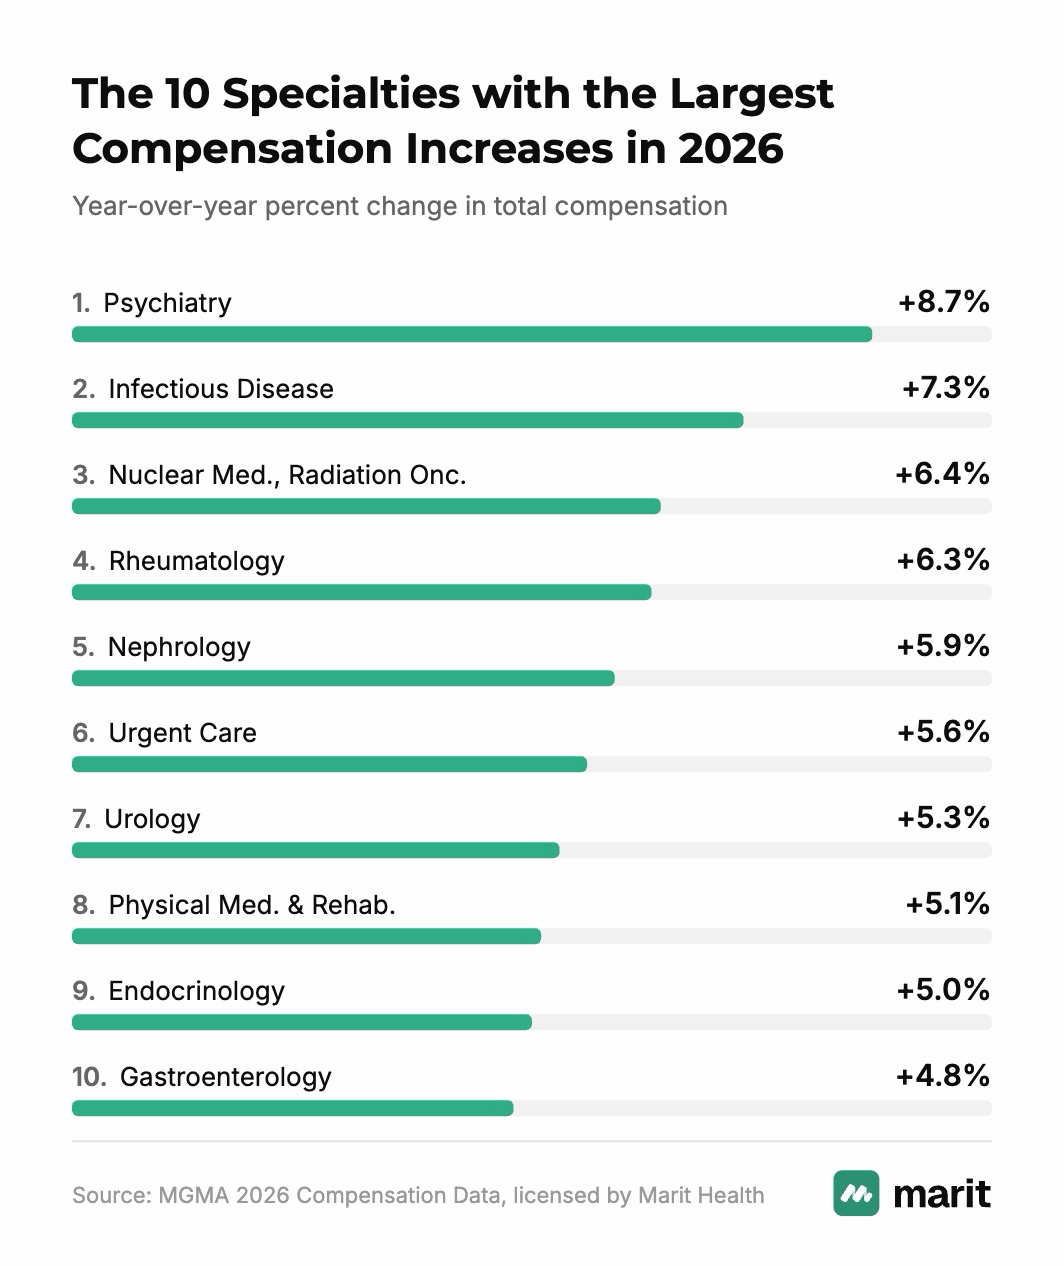
The Medical Group Management Association (MGMA) salary data represents the gold standard for healthcare compensation benchmarking, providing comprehensive metrics derived from thousands of medical practices across the United States to help organizations establish fair market value for physicians, advanced practice providers, and administrative staff.
The Significance of MGMA Salary Benchmarks in Modern Healthcare
The Medical Group Management Association stands as the nation's premier association for professional administrators and executives of medical group practices. For decades, its compensation and productivity surveys have functioned as the foundational benchmark for healthcare organizations, private practices, health systems, and academic medical centers. When stakeholders discuss compensation benchmarking within the medical sector, they are almost universally referring to the data compiled, analyzed, and published annually by this organization.
Understanding this data requires recognizing the operational mechanics behind how it is collected and structured. Unlike generic salary aggregation websites that scrape unverified job postings or rely on self-reported estimates, MGMA gathers its figures directly from the financial and human resources departments of healthcare organizations nationwide. This direct-source methodology ensures that the metrics reflect actual compensation packages, including base salaries, productivity bonuses, call pay, signing bonuses, and fringe benefits.
Healthcare executives, physician recruiters, healthcare attorneys, and clinicians themselves rely on these figures to navigate the complex regulatory and economic realities of medical practice. In an industry heavily governed by federal compliance laws—such as the Stark Law and the Anti-Kickback Statute—establishing fair market value (FMV) is not merely a best practice; it is a strict legal requirement. Utilizing verified benchmarks ensures that physician contracts withstand legal scrutiny and protect organizations from severe penalties associated with above- or below-market compensation arrangements.
Core Components of MGMA Compensation Surveys
The architecture of an MGMA data release is comprehensive, spanning multiple distinct survey reports tailored to specific segments of the healthcare workforce. Navigating these reports requires a firm grasp of the core metrics utilized throughout the industry. The surveys are generally partitioned into physician compensation, provider compensation for advanced practice providers, and management and staff compensation.
Within each report, data is sliced across various dimensions to provide granular context. A single medical specialty does not command a uniform salary across the entire country; variables such as geographic region, practice ownership model, practice size, and collection-to-charge ratios heavily influence total compensation. Consequently, users of the data must understand how to interpret percentiles, productivity metrics, and compensation models.
Key Metrics Found in Reports
- Total Compensation: The aggregate of all cash compensation, including base salary or hourly wages, productivity bonuses, medical directorship stipends, research stipends, and call pay received over a calendar year.
- Collections and Productivity: Measured typically in Work Relative Value Units (wRVUs), net patient revenue, or gross charges, reflecting the actual clinical output generated by the provider.
- Practice Ownership Models: Distinctions between physician-owned practices, hospital-owned clinics, and integrated health systems, which often exhibit distinct compensation philosophies and overhead structures.
- Geographic Variations: Regional, state-level, and metropolitan adjustments that account for local cost of living and labor market dynamics.
Physician Compensation Benchmarking
Physician compensation remains the most frequently consulted segment of the MGMA data portfolio. The medical landscape features vast disparities in earning potential, driven by years of specialized training, market demand, and revenue generation capacity. Primary care physicians, such as family medicine and internal medicine practitioners, operate on different economic models compared to surgical subspecialists like orthopedic surgeons, neurosurgeons, and cardiothoracic surgeons.
When evaluating physician compensation through these benchmarks, organizations look closely at the ratio between fixed base pay and variable productivity bonuses. Many modern employment contracts utilize a hybrid model where a physician receives a guaranteed base salary for a defined period, coupled with an incentive bonus tied directly to wRVU generation once a specific threshold is cleared.
Furthermore, the data helps illuminate trends regarding subspecialty valuation. For instance, diagnostic radiologists, gastroenterologists, and invasive cardiologists consistently rank near the top of compensation surveys due to the high-revenue procedures they perform and the relative scarcity of qualified specialists. Conversely, pediatric subspecialties and certain primary care disciplines often see lower compensation figures relative to their training duration, reflecting broader systemic reimbursement structures within public and private insurance markets.
Advanced Practice Providers (APPs)
In recent years, the role of Advanced Practice Providers—including Nurse Practitioners (NPs), Physician Assistants (PAs), and Certified Registered Nurse Anesthetists (CRNAs)—has expanded dramatically. As healthcare delivery models shift toward team-based care and outpatient access points multiply, compensation tracking for APPs has become essential for medical group sustainability.
MGMA surveys track APP compensation across various specialties, examining how surgical support APPs differ from primary care or urgent care counterparts. Because APPs significantly impact patient volume and practice revenue, organizations increasingly tie a portion of their compensation to productivity metrics such as patient encounters or wRVUs, moving away from purely fixed-salary structures. Analyzing these benchmarks allows practices to remain competitive in recruiting top-tier clinical talent while maintaining sustainable operating margins.
Management and Administrative Staff Salaries
Beyond clinical staff, medical group success relies heavily on competent leadership and operational support. The management and staff compensation survey covers a vast spectrum of non-clinical roles essential to running a medical practice, ranging from C-suite executives down to front-desk receptionists and medical billers.
Positions tracked in these reports include:
- Chief Executive Officers (CEOs) and Chief Operating Officers (COOs) of large medical groups.
- Practice Managers and Clinic Administrators overseeing daily operations.
- Billing and Coding Supervisors, alongside revenue cycle specialists.
- Registered Nurses (RNs), Medical Assistants (MAs), and patient service representatives.
Salary data for these roles is typically broken down by practice size (measured by the number of full-time equivalent physicians) and revenue thresholds. This allows a small independent clinic with three physicians to accurately benchmark administrative salaries differently than a massive multi-specialty health system employing hundreds of providers.
Comparative Overview of Survey Categories
| Survey Category | Primary Target Audience | Key Metrics Analyzed | Typical Use Case |
|---|---|---|---|
| Physician Compensation | Physicians, Recruiters, Executives | Total compensation, wRVUs, base salary, call pay | Contract negotiation, Fair Market Value (FMV) compliance |
| Advanced Practice Providers | NPs, PAs, CRNAs, HR Managers | Hourly rates, annual salary, productivity bonuses | Setting competitive compensation for clinical extenders |
| Management & Staff | Practice Managers, C-Suite Executives | Supervisory salaries, administrative pay scales, turnover rates | Budgeting, operational cost control, market adjustments |
| Practice Operations | Financial Officers, Consultants | Operating cost per physician, overhead ratios, staffing ratios | Operational efficiency audits, financial planning |
Methodological Considerations and Data Interpretation
Interpreting medical compensation data requires careful attention to statistical methodology. A common pitfall among inexperienced analysts is relying solely on the mathematical average (mean) rather than examining the median and the interquartile range (25th to 75th percentiles). Because a small number of extremely high-earning specialists can skew the mean upward, the median provides a far more reliable indicator of typical market compensation.
Additionally, users must account for the timing of data releases. Surveys reflect historical data collected during previous reporting periods, meaning that rapid macroeconomic shifts, inflation spikes, or legislative changes in healthcare reimbursement may not be instantly reflected in the published figures. Healthcare organizations often apply localized cost-of-living adjustments or inflationary projections when utilizing older survey data for active recruitment cycles.
Another critical consideration involves distinguishing between total cash compensation and total rewards. Total rewards encompass non-cash benefits such as employer-sponsored retirement contributions, malpractice insurance coverage, continuing medical education (CME) allowances, and health insurance. When evaluating an offer against benchmark data, both parties must verify whether the cited figures include these auxiliary benefits.
Legal and Regulatory Compliance (Fair Market Value)
The primary reason healthcare organizations subscribe to and utilize these benchmarks is regulatory compliance. Under federal law, physician compensation arrangements must reflect Fair Market Value (FMV) and commercial reasonableness. If a health system pays a physician significantly above market rate for clinical services, federal regulators may view the excess compensation as an illegal inducement for patient referrals, violating the Stark Law or the federal Anti-Kickback Statute.
Conversely, paying below market value can lead to recruitment failures and potential private-inurement issues for non-profit entities. Utilizing robust, third-party survey data establishes a defensible compliance defense. In the event of a federal audit or whistleblower lawsuit, demonstrating that compensation was set by referencing recognized industry surveys like those from the Medical Group Management Association provides objective proof that payments were commercially reasonable and reflective of legitimate market rates.
Frequently Asked Questions
What is the difference between mean and median in compensation surveys?
The mean is the mathematical average calculated by summing all reported salaries and dividing by the total number of respondents. The median is the exact middle point of the data set when all figures are arranged in sequential order. In healthcare compensation, the median is generally preferred because it is less affected by statistical outliers earning exceptionally high or low amounts.
How often are compensation reports updated?
Comprehensive surveys are typically published annually, capturing financial data from the preceding calendar year. Some sectors may feature pulse surveys or specialized update modules, but the primary benchmarking datasets follow an annual release schedule.
Are all medical groups required to participate in the surveys?
Participation is voluntary. Medical groups, hospitals, and integrated delivery networks choose to submit their internal compensation and operational data, often receiving discounted access to the final published reports in exchange for their participation.
How do wRVUs affect physician take-home pay?
Work Relative Value Units measure the time, technical skill, and mental effort required of a physician for a specific clinical service. In productivity-based compensation models, physicians earn a predetermined dollar amount per wRVU generated, allowing high-volume or highly efficient clinicians to earn significantly above their base salary.
Can non-members purchase these reports?
Yes, non-members can purchase the published data reports, though Medical Group Management Association members typically receive preferred pricing and access to interactive online data dive tools that allow for customized filtering by region, specialty, and practice size.
Practical Next Steps for Compensation Planning
Organizations and individuals navigating healthcare compensation should begin by identifying the specific survey report that aligns with their operational scope or career specialty. Healthcare administrators should cross-reference internal payroll figures against regional medians to identify potential retention risks or compliance vulnerabilities. Meanwhile, physicians and advanced practice providers preparing for contract renewals should examine the 50th and 75th percentiles for their exact specialty and geographic region to establish realistic expectations during negotiations. Always consult qualified legal and financial professionals to ensure all compensation structures fully comply with applicable federal and state regulatory frameworks.