A labelled humerus is a standard anatomical model, diagram, or digital rendering that clearly identifies the key bony landmarks, borders, surfaces, and articulating structures of the human upper arm bone. By displaying precise labels for features such as the greater and lesser tubercles, the surgical and anatomical necks, and the distal epicondyles, these visual aids serve as indispensable educational tools for students, medical professionals, and educators studying human osteology.
Introduction to the Humerus and Its Anatomical Context
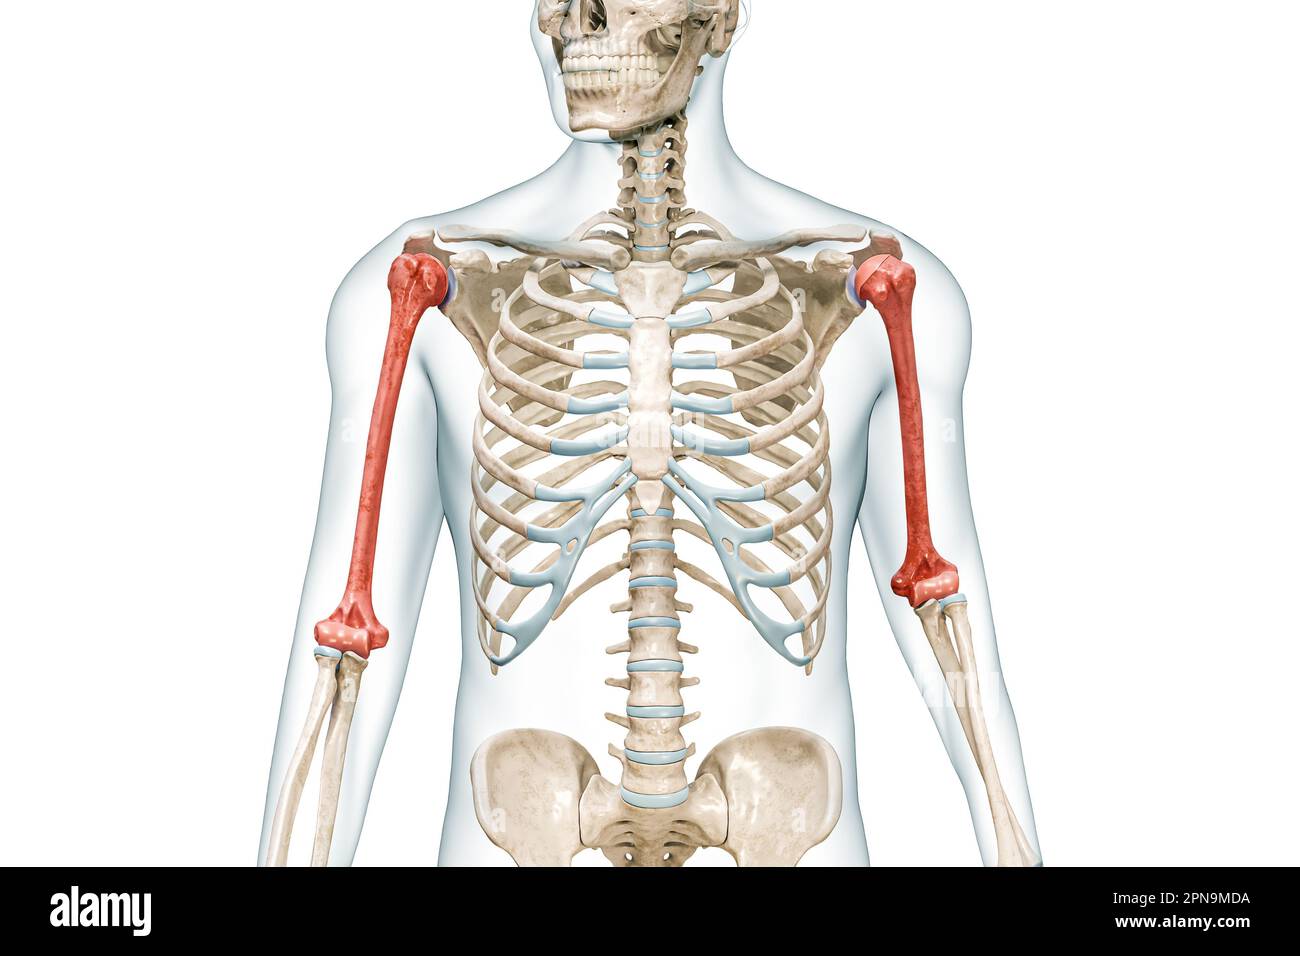
The humerus is the longest and largest bone in the upper extremity, acting as the structural pillar of the arm from the shoulder down to the elbow. In anatomical education, clinical training, and orthopedic practice, mastering the intricate topography of this bone is essential. Because the humerus serves as a critical anchor point for numerous muscles, ligaments, and tendons, and because it plays a primary role in complex multi-axial movements at the glenohumeral joint and hinge movements at the elbow, having a reliable, labelled humerus reference is vital.
Whether examining a physical osteological specimen in a university laboratory or interacting with a three-dimensional digital model in a virtual anatomy suite, learners rely on clear labels to orient themselves. The bone features a complex proximal end that interfaces with the scapula, a long central shaft characterized by distinct borders and surfaces, and an expanded distal end that forms the articulating components of the elbow joint. Understanding these regions requires a systematic breakdown of each anatomical feature, its precise location, and its functional or clinical importance.
Proximal Extremity: The Shoulder Articulation and Stabilization Landmarks
The proximal end of the humerus is engineered to fit into the shallow glenoid cavity of the scapula, providing a wide range of motion at the cost of inherent joint stability. A properly labelled humerus highlights several crucial landmarks in this region, each serving a distinct mechanical or soft-tissue attachment role.
The Head of the Humerus and Neck Variations
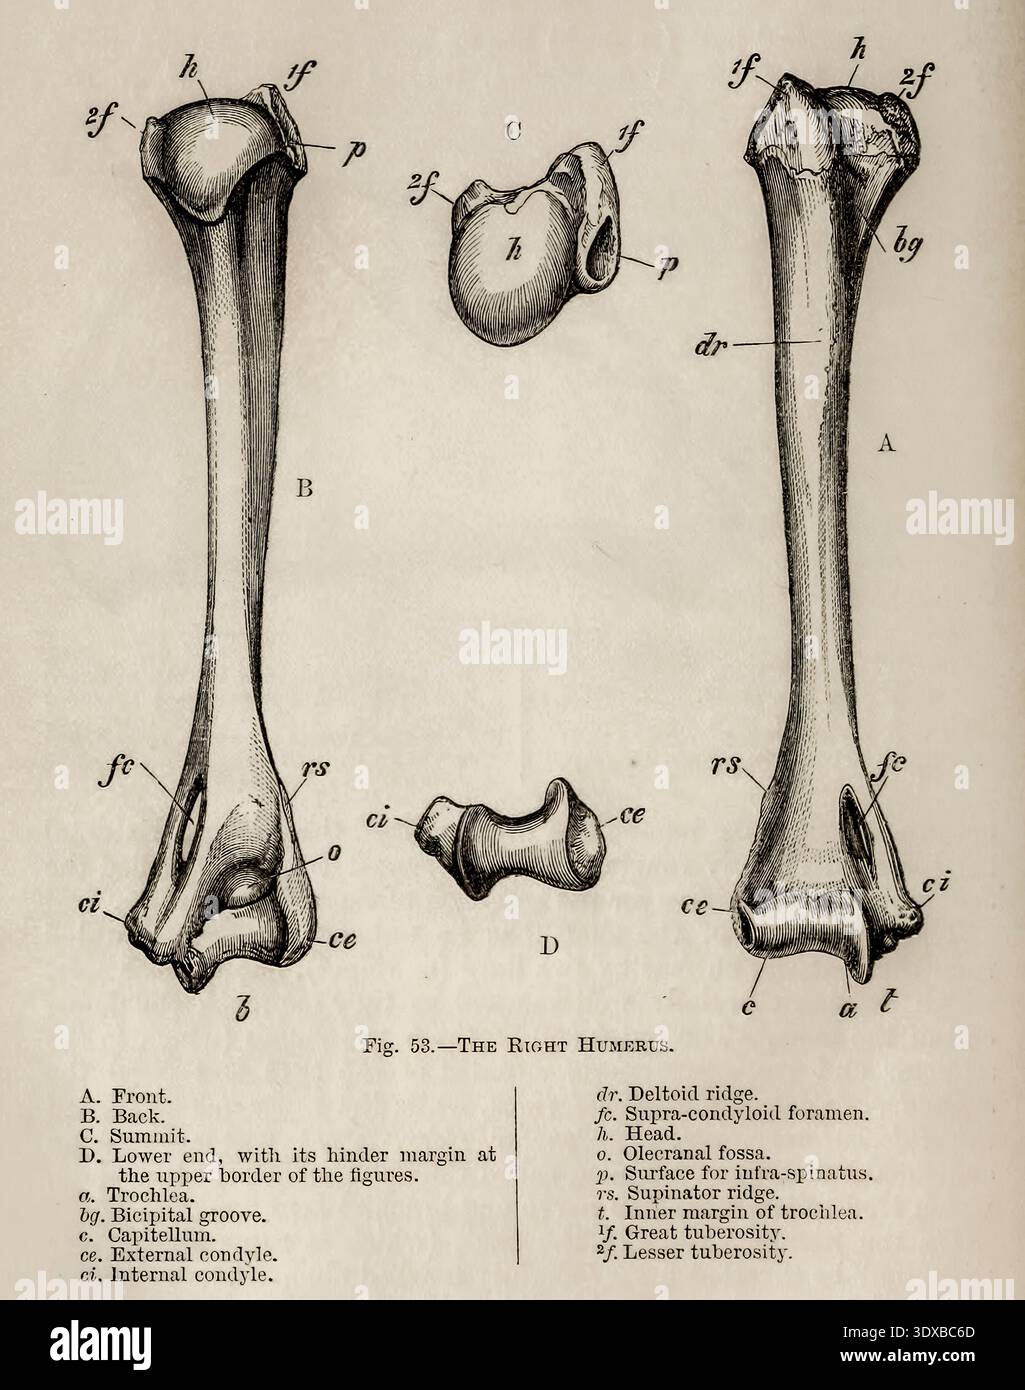
At the most proximal and medial aspect lies the head of the humerus, a smooth, hemispherical articular surface covered in hyaline cartilage that articulates with the glenoid fossa. Circling the base of this articular surface is the anatomical neck, a slight constriction that separates the head from the greater and lesser tubercles.
Just distal to the tubercles lies the surgical neck, a frequent site of clinical concern, particularly in geriatric populations experiencing fragility fractures due to falls. The surgical neck is designated as "surgical" because it represents a common transition zone where fractures frequently occur and require surgical intervention.
Tubercles and Intertubercular Sulcus
The proximal shaft features two prominent bony prominences that serve as muscle insertion sites:
- Greater Tubercle: Located on the lateral aspect of the proximal humerus, it provides attachment for the supraspinatus, infraspinatus, and teres minor muscles of the rotator cuff.
- Lesser Tubercle: Located more anteriorly and medially, it serves as the insertion point for the subscapularis muscle.
- Intertubercular Sulcus (Bicipital Groove): The deep groove separating the greater and lesser tubercles. This pathway houses the tendon of the long head of the biceps brachii muscle as it ascends toward the supraglenoid tubercle of the scapula. The lips of this sulcus—the crests of the greater and lesser tubercles—serve as insertion sites for the latissimus dorsi, pectoralis major, and teres major muscles.
| Landmark Name | Anatomical Location | Primary Function or Soft-Tissue Attachment |
|---|---|---|
| Head of Humerus | Proximal, medial surface | Articulates with the glenoid cavity of the scapula |
| Anatomical Neck | Circumference just distal to the head | Attachment boundary for the articular capsule |
| Surgical Neck | Tapered region distal to the tubercles | Common site for proximal humerus fractures |
| Greater Tubercle | Lateral aspect of proximal region | Insertion for supraspinatus, infraspinatus, teres minor |
| Lesser Tubercle | Anterior/medial aspect of proximal region | Insertion for the subscapularis muscle |
| Bicipital Groove | Between greater and lesser tubercles | Passage for the tendon of the long head of biceps brachii |
The Shaft of the Humerus: Borders, Surfaces, and Muscle Attachments
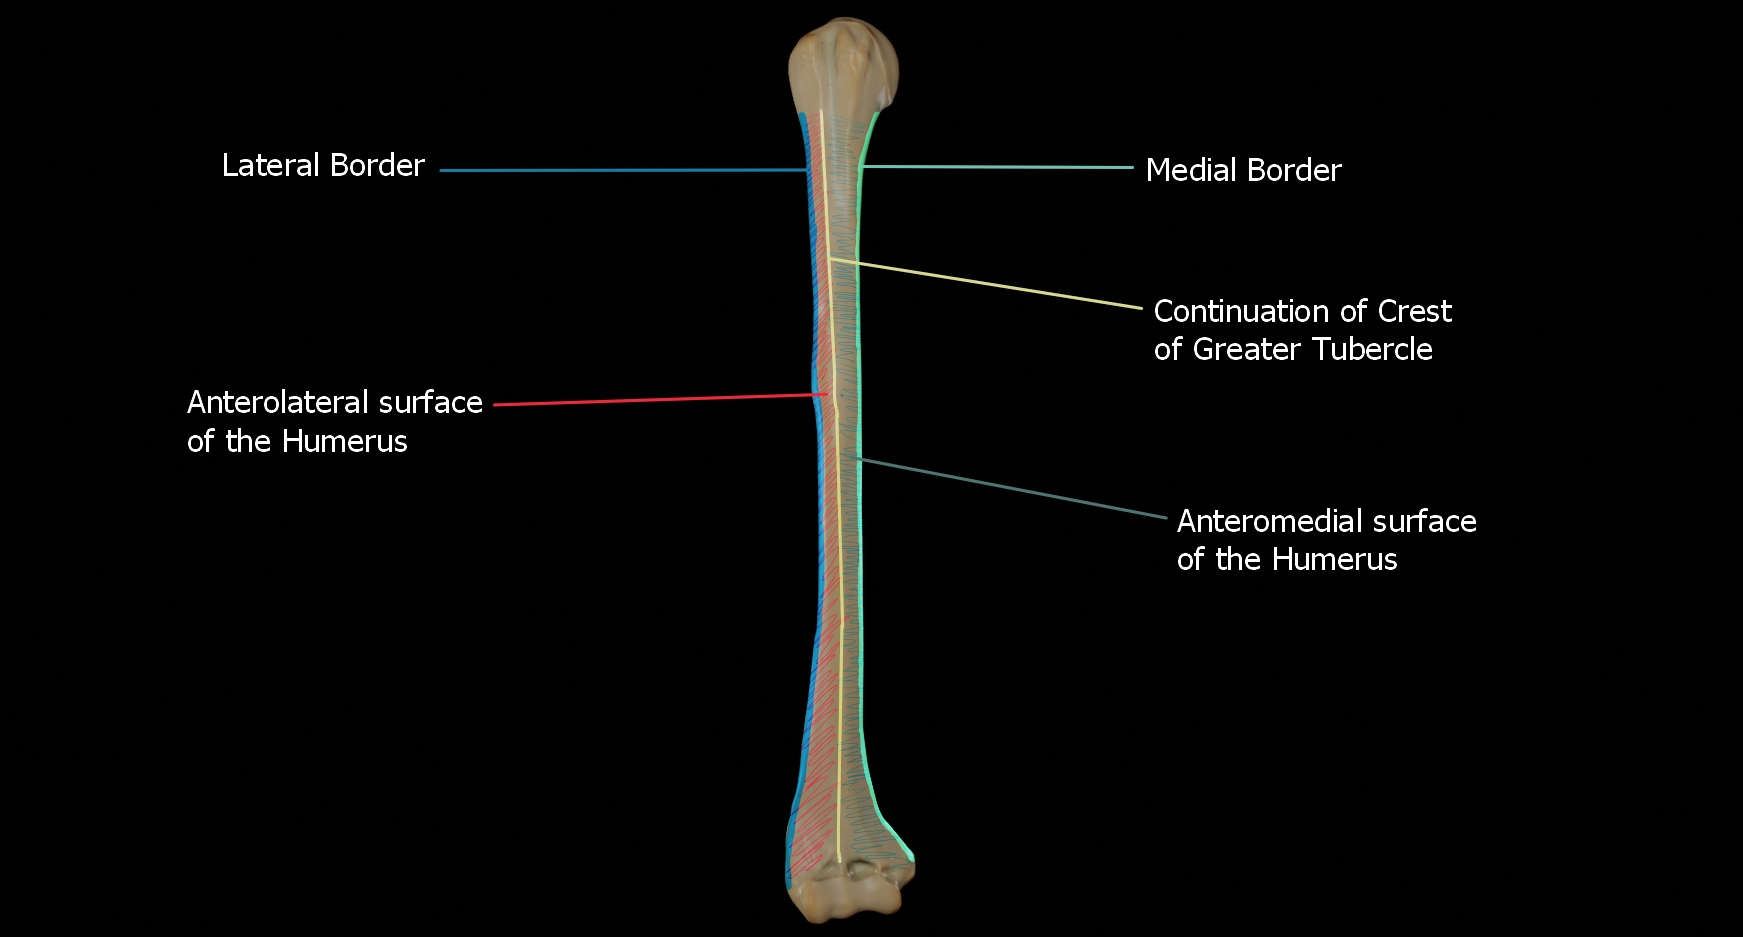
Distal to the proximal landmarks, the shaft of the humerus transitions from a cylindrical shape proximally to a more triangular shape distally. A labelled humerus diagram maps out three distinct borders and three surfaces to help clinicians and students describe the precise location of pathological lesions, surgical incisions, or fracture patterns.
Surfaces of the Shaft
- Anterolateral Surface: Located between the anterior and lateral borders, this surface features a prominent, rough, V-shaped area known as the deltoid tuberosity. This tuberosity is the primary insertion site for the deltoid muscle, which abducts the arm.
- Anteromedial Surface: Extending between the anterior and medial borders, this surface features the continuation of the intertubercular groove proximally and serves as an attachment area for portions of the coracobrachialis muscle.
- Posterior Surface: Situated between the lateral and medial borders, this broad surface is dominated by the spiral groove (or radial groove). The radial nerve and profunda brachii artery travel diagonally across the posterior surface within this groove, making them vulnerable to mid-shaft humeral fractures.
Borders of the Shaft
The borders—anterior, medial, and lateral—provide the structural lines of separation between the surfaces. The lateral and medial borders terminate distally in the lateral and medial supracondylar ridges, which flare out to form the broad distal expansion of the bone.
Distal Extremity: The Elbow Complex and Articular Surfaces
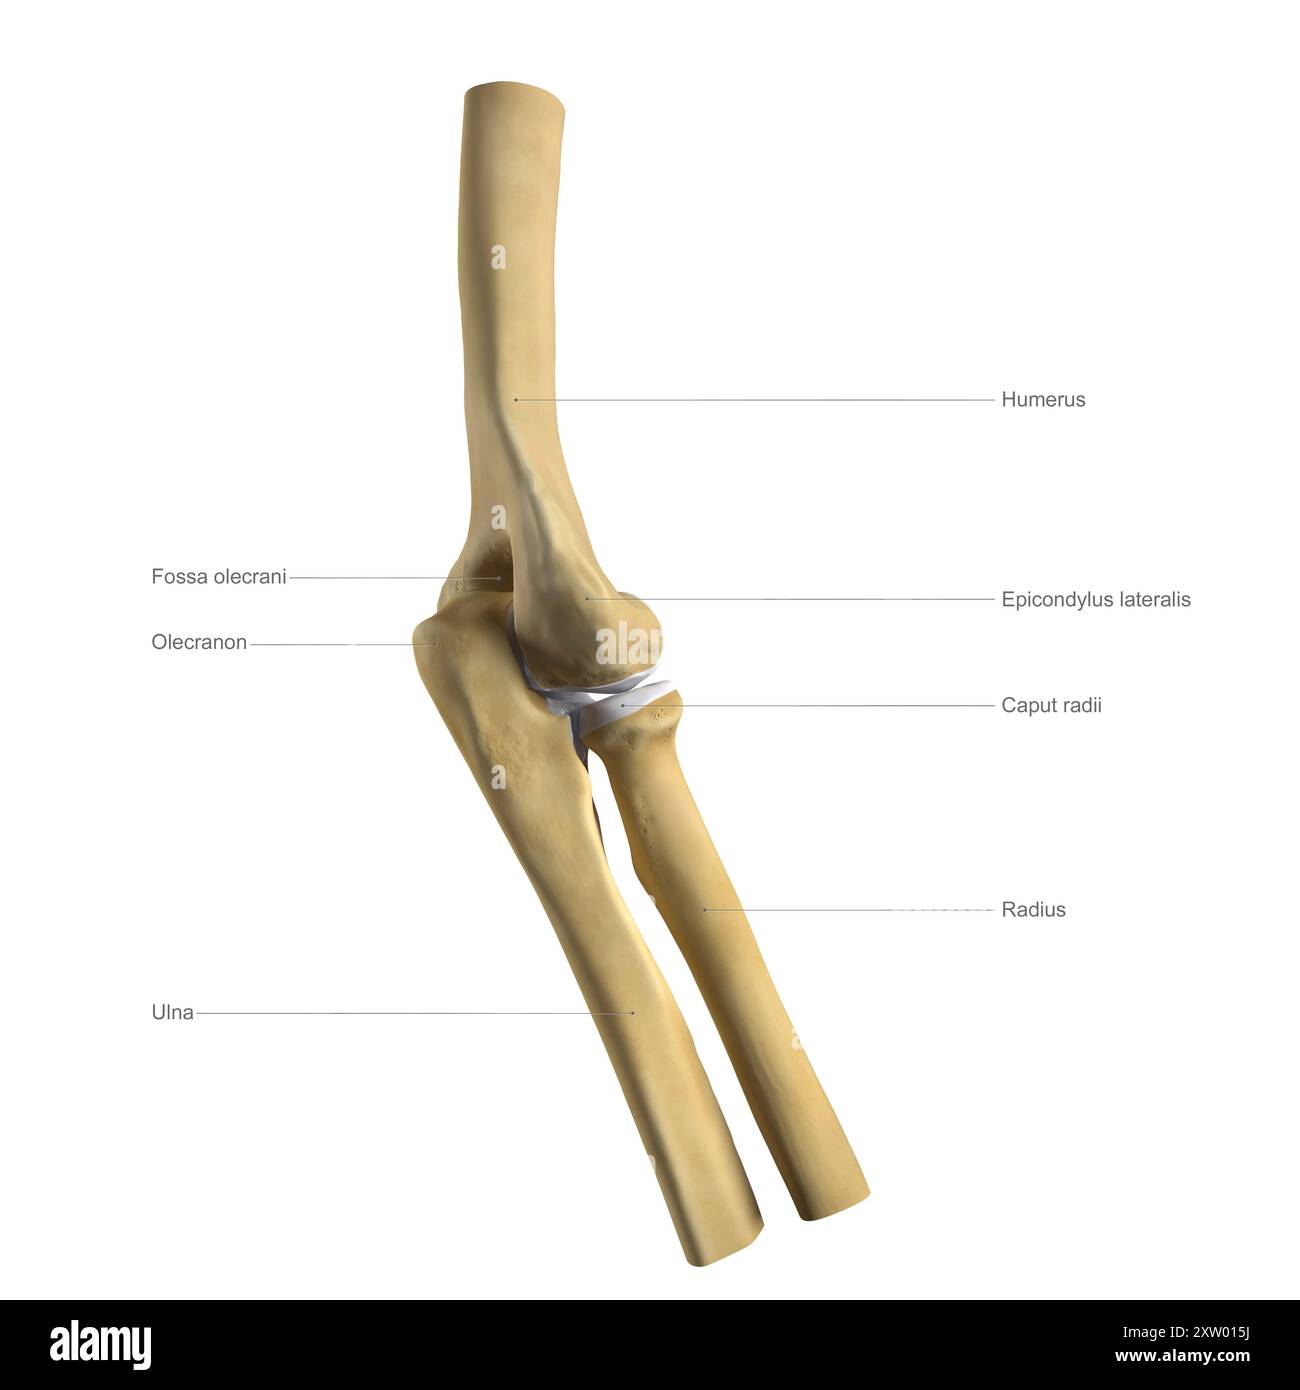
The distal end of the humerus broadens transversely to form the condyle, which includes both articular surfaces and non-articular bony prominences designed to facilitate forearm movement and stabilize the elbow joint.
Articular Structures
- Trochlea: A spool-shaped surface located on the medial side of the distal humerus that articulates with the trochlear notch of the ulna, forming the primary hinge mechanism of the elbow.
- Capitulum: A smooth, rounded, ball-like eminence on the lateral side that articulates with the superior concave surface of the head of the radius.
Non-Articular Fossae and Epicondyles
To accommodate the movements of the forearm bones during extreme flexion and extension, the distal humerus features three shallow depressions:
- Coronoid Fossa: Located on the anterior aspect directly above the trochlea, receiving the coronoid process of the ulna during full elbow flexion.
- Radial Fossa: Positioned just superior to the capitulum on the anterior side, accommodating the head of the radius during flexion.
- Olecranon Fossa: A deep depression located on the posterior aspect of the distal humerus that receives the olecranon process of the ulna when the elbow is fully extended.
Flanking these articular structures are the medial epicondyle and lateral epicondyle. The medial epicondyle is particularly prominent and serves as the origin for the common flexor tendon of the forearm, as well as protecting the ulnar nerve as it passes posteriorly through the cubital tunnel. The lateral epicondyle serves as the common extensor origin for the superficial extensor muscles of the forearm.
Clinical Relevance and Pathological Considerations
A thorough understanding of a labelled humerus extends far beyond academic memorization; it is fundamental to diagnosing and treating upper extremity trauma and pathology. Medical professionals rely on this anatomical map to interpret radiographic imaging, plan surgical approaches, and assess nerve vulnerability.
Fracture Patterns and Nerve Vulnerability
Because of the distinct anatomical landmarks of the humerus, specific fracture locations frequently jeopardize adjacent neurovascular structures:
- Proximal Fractures: Fractures involving the surgical neck can injure the axillary nerve and the posterior circumflex humeral artery as they course around the surgical neck within the quadrangular space.
- Mid-shaft Fractures: Fractures along the humeral shaft—frequently sustained during direct trauma or motor vehicle accidents—pose a direct risk to the radial nerve and profunda brachii artery as they travel through the radial groove. Damage to the radial nerve leads to classic wrist drop and sensory deficits over the dorsum of the hand.
- Supracondylar Fractures: Common in pediatric populations, these fractures can compromise the median nerve and the brachial artery, necessitating prompt evaluation to prevent ischemic contractures such as Volkmann's ischemic contracture.
Surgical Approaches and Biomechanics
Orthopedic surgeons utilize specific internervous planes based on the borders and surfaces of the humerus when performing internal fixation with plates and screws or intramedullary nailing. Recognizing the exact boundaries of muscle insertions, such as the deltoid and pectoralis major, helps minimize soft-tissue stripping and preserves vascularity to the bone segments, promoting optimal fracture healing.
Practical Applications in Education and Verification
For students and educators utilizing physical models or digital anatomical atlases, verifying the accuracy of a labelled humerus ensures correct foundational knowledge. High-quality educational models consistently highlight the following diagnostic and instructional checkpoints:
- Laterality Determination: Knowing how to determine whether a humerus is left or right (head pointing medially, lesser tuberosity facing anteriorly, and olecranon fossa facing posteriorly).
- Proportional Landmark Location: Identifying the relative vertical positioning of the deltoid tuberosity at the midpoint of the lateral shaft versus the distal epicondyles.
- Neurovascular Corridors: Mapping nerve pathways directly onto the bone surfaces to anticipate clinical complications during trauma.
Disclaimer: This article is intended for educational and informational purposes only and does not substitute for professional medical advice, clinical diagnosis, or surgical training.